The word “proctologist” does not by itself prove colorectal training, surgical experience, or sound diagnostic judgment. By checking registration, matching the clinician to your symptoms, assessing the first consultation, and comparing treatment recommendations, you can choose care based on competence rather than clinic slogans.
Key takeaways
- Verify the doctor’s registration number with the NMC and Maharashtra Medical Council.
- Choose a specialist whose experience matches your symptoms and urgency.
- Ask what examination and investigations are necessary before accepting treatment.
- Compare evidence, risks, recovery time, and alternatives—not marketing claims.
Verify the doctor’s training, registration, and actual specialty
Start with the doctor’s registration number, not the word “proctologist.” Search the National Medical Commission’s medical register and, in Maharashtra, the Maharashtra Medical Council register. Confirm that the name, qualification, registration number, and registration status match the doctor treating you.
Ask the clinic for written details of the doctor’s proctologist qualifications. Check for:
- MBBS from a recognised medical college
- MS General Surgery or DNB General Surgery
- Fellowship or focused postgraduate training in colorectal surgery, proctology, or anorectal surgery
- Current medical registration and any claimed board certification, verified with the issuing body
MS General Surgery and DNB General Surgery establish surgical training, but neither alone proves advanced colorectal specialisation. A fellowship, formal colorectal training, or a practice devoted substantially to anorectal surgery provides stronger evidence for complex fistulas, recurrent disease, and failed previous operations.
Confirm the doctor’s actual specialty during booking. Ask, “What percentage of your practice involves anorectal conditions, and where did you complete your colorectal or proctology training?” A general surgeon may competently treat common piles or abscesses, while a colorectal surgeon has additional focused training; the title alone does not distinguish them.
Treat unverifiable credentials, vague claims such as “expert,” or refusal to disclose registration details as reasons to seek another opinion. If you have severe pain, fever, spreading swelling, heavy bleeding, faintness, or difficulty passing urine, obtain urgent medical assessment instead of delaying care to compare profiles.
Match the specialist to your symptoms and urgency
Choose a general surgeon or proctologist for straightforward piles or fissures, but choose a colorectal surgeon for fistulas, recurrent disease, complex operations, or suspected cancer. “Proctologist” commonly describes a colorectal surgeon, yet the title alone does not prove formal colorectal training.
| Problem or warning sign | Best starting clinician | Why |
|---|---|---|
| Typical piles or fissure | General surgeon or proctologist | Can examine, confirm the diagnosis, and offer medical or procedural treatment |
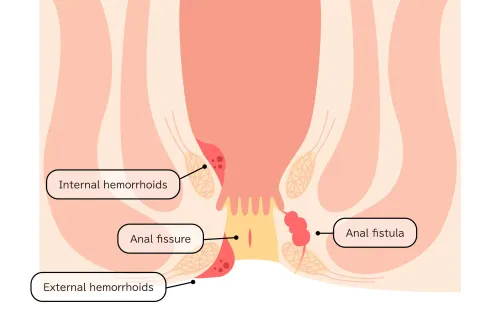
| Fistula, recurrent abscess, or failed surgery | Colorectal surgeon or proctologist with colorectal training | Treatment depends on the tract’s relationship to the anal sphincter; cutting too much muscle can impair continence |
| Rectal bleeding | Proctologist, colorectal surgeon, or gastroenterologist | Bleeding is not automatically hemorrhoids; examination, anoscopy, and sometimes colonoscopy are needed |
| Suspected colorectal or anal cancer | Colorectal surgeon and gastroenterologist | They can coordinate biopsy, colonoscopy, staging, and specialist treatment |
| Ayurvedic treatment preference | Ayurvedic practitioner only after diagnosis | Do not delay surgical assessment for heavy bleeding, fever, severe pain, or a growing lump |
Seek urgent care for heavy bleeding, faintness, black stools, fever with anal swelling, or rapidly worsening pain. Ask whether the clinician performs a digital rectal examination and anoscopy, and how they handle colonoscopy referral.
A provider who proposes piles treatment without examining you or considering fissure, abscess, inflammatory bowel disease, infection, or cancer is the wrong choice.
Measure direct anorectal experience before you book
Ask for specific numbers, not “many procedures”: the surgeon’s annual case volume for anorectal operations and the procedures performed most often. A high total surgical volume does not prove strong proctology experience if only a small share involves the anus and rectum.
- Ask how many patients the surgeon treats each year for hemorrhoids, anal abscesses, complex anal fissure, fistula, and rectal bleeding.
- Ask how often they manage a recurrent fistula, especially one involving the anal sphincter, and how they choose between fistulotomy, staged treatment, seton placement, or sphincter-sparing procedures.
- Ask how they handle operations that have already failed, including recurrent hemorrhoids, persistent fissure, wound problems, or repeat fistula surgery.
- Ask about continence assessment before sphincter-related surgery. Prior childbirth injury, existing leakage, and sphincter damage can change the safest plan.
- Ask for the surgeon’s typical rates of recurrence, infection, reoperation, and new gas or stool leakage for the proposed procedure.
- Ask who provides follow-up if symptoms persist and what happens when the first treatment does not work.
A trustworthy surgeon answers these questions plainly and explains when imaging, examination under anaesthesia, colorectal referral, or a second opinion is appropriate. Be cautious if the doctor promises a permanent cure, recommends surgery without examining you, or cannot distinguish hemorrhoids from fissure, abscess, fistula, inflammatory bowel disease, skin disease, sexually transmitted infection, or cancer.
Judge the first consultation by the examination and investigation plan
The first consultation should include a symptom history, a physical examination, and a reasoned plan to rule out more than hemorrhoids. The clinician should ask about bleeding, pain, discharge, bowel habits, straining, weight loss, fever, medicines, family history, and previous anorectal procedures. Persistent or unexplained bleeding must not be labelled piles without investigation.
Ask the clinician to explain:
- Whether a digital rectal examination is appropriate and what it will assess.
- Whether anoscopy or proctoscopy is needed to inspect the anal canal and lower rectum.
- Which diagnosis is being considered, including fissure, abscess, fistula, inflammatory bowel disease, sexually transmitted infection, skin disease, or cancer.
- What result would trigger referral, biopsy, imaging, or colonoscopy.
- Whether a complete blood count is needed to check for anaemia or infection.
| Investigation | What it can clarify | When it might be necessary |
|---|---|---|
| Digital rectal examination | Masses, tenderness, sphincter tone, and blood | Bleeding, pain, altered bowel habits, or suspected mass |
| Anoscopy | Hemorrhoids, fissures, inflammation, and anal lesions | Suspected anal-canal disease |
| Proctoscopy | Lesions and inflammation farther inside the rectum | Rectal bleeding or unexplained symptoms |
| Complete blood count | Anaemia or infection | Ongoing bleeding, fatigue, fever, or suspected abscess |
| Colonoscopy or biopsy | Polyps, inflammatory disease, or cancer | Risk factors, persistent bleeding, abnormal findings, or failed prior evaluation |
A treatment recommendation made without an appropriate examination or differential diagnosis deserves a second opinion.
Compare treatment recommendations instead of choosing a marketing claim
A recommended procedure earns your consent only when the doctor compares it with observation, medication, office treatment, and other operations. Ask for expected pain, recovery time, anesthesia, continence effects, recurrence risk, total follow-up, and the plan if the first treatment fails.
| Option | Compare before choosing | Questions to ask |
|---|---|---|
| Observation or medication | Avoids procedure risks but may not resolve prolapse, abscess, or persistent symptoms | What finding makes waiting unsafe, and when will you reassess? |
| Office treatment | Rubber-band ligation suits many grade I–II internal hemorrhoids and selected grade III cases; repeat sessions may be needed | How many sessions are likely, and what happens if bleeding or prolapse returns? |
| Excisional surgery | More painful recovery, but often more definitive for large external or advanced prolapsing hemorrhoids | How many days away from work, and what pain-control plan will you use? |
| Sphincter-sparing fistula treatment | Protects continence when the tract crosses substantial sphincter muscle, but staged care or recurrence remains possible | Where does the tract lie, and will imaging change the operation? |
| Minimally invasive treatment or laser surgery | Smaller wounds do not automatically mean lower recurrence risk or faster recovery | Show outcome data for my diagnosis, not a general promotional claim. |
| Ayurvedic treatment | Ask for evidence for the specific product, independent testing, medicine interactions, and whether it could delay diagnosis | What ingredients are present, and how will you investigate persistent bleeding? |
Shree Hospital - 08048060809 can be one clinic you ask to document these comparisons, including its rationale for Ksharsutra treatment for fistula. Also ask how rectal bleeding is evaluated and when colonoscopy or cancer referral is needed; average-risk screening starts at age 45 in USPSTF guidance.
Frequently asked questions
How can I verify whether a proctologist is properly registered?
Search the National Medical Commission medical register and, in Maharashtra, the Maharashtra Medical Council register. Match the doctor’s name, qualification, registration number, and status.
How do I choose a specialist for my anorectal symptoms?
Match the doctor’s expertise to your symptoms, such as piles, fissures, fistulas, bleeding, pain, or a suspected abscess. Seek urgent assessment for severe pain, fever, heavy bleeding, or rapidly increasing swelling.
What should happen during the first proctology consultation?
The doctor should take a focused history, perform an appropriate anorectal examination, explain why each investigation is needed, and give you a clear treatment plan.
How should I compare different treatment recommendations?
Compare the diagnosis, expected benefit, risks, recovery time, follow-up needs, alternatives, and consequences of delaying treatment. Do not choose solely on claims such as painless, laser, or permanent.